
Should My Clinic Use an AI Bot to Book Appointments? (The Show-Rate Data Says Not Yet — Automate Around Humans Instead)
Every cash-pay practice owner is hearing the same pitch right now: let AI answer your leads and book your appointments.
We’ve tested it — at scale, at the biggest weight-loss clinic in our portfolio.
The result: appointments booked by the AI showed up around 20% of the time. Appointments booked by a human: around 90%.
Here’s the FAQ on where AI booking actually stands, what to automate instead, and how one multi-location clinic grew from 360 to about 400 patients in a month with humans firmly in charge of the calendar.
Should my clinic use an AI bot to book appointments?
Not yet.
Our verdict from real production data: “It sucks… I just haven’t found that it’s quite there yet. I’m very optimistic that it will get there, but I haven’t found that it quite is yet.”
This isn’t a hypothetical.
The largest weight-loss client we work with — a medspa we helped add $6.7M in revenue in a single year actually ran AI appointment booking on real lead flow.
“Their attendance rate is like 20% or something. If a human books the appointment, it’s like 90%.”
A booking that doesn’t show isn’t a booking.
It’s a calendar hole that cost you a lead.
At those show rates, the AI wasn’t reducing staffing cost — it was converting ad spend into no-shows.
Why do AI-booked patients no-show so much?
Because the booking happens without rapport or accountability — nobody made a commitment to a person.
A human booking is a micro-promise: someone asked about your Tuesday, you said 2pm works, they said see you then.
An AI booking is a form-fill with extra steps.
The clinic lead on this call had tested an AI intake herself as a patient-side experience.
The conversation was thorough, and then — “I never heard anything.”
No follow-through, no ownership, no person on the other end who notices when you don’t confirm.
The technology handles the conversation.
It doesn’t yet create the obligation.
Show-rate is a relationship metric wearing an operations costume.
What should I automate instead of the booking conversation?
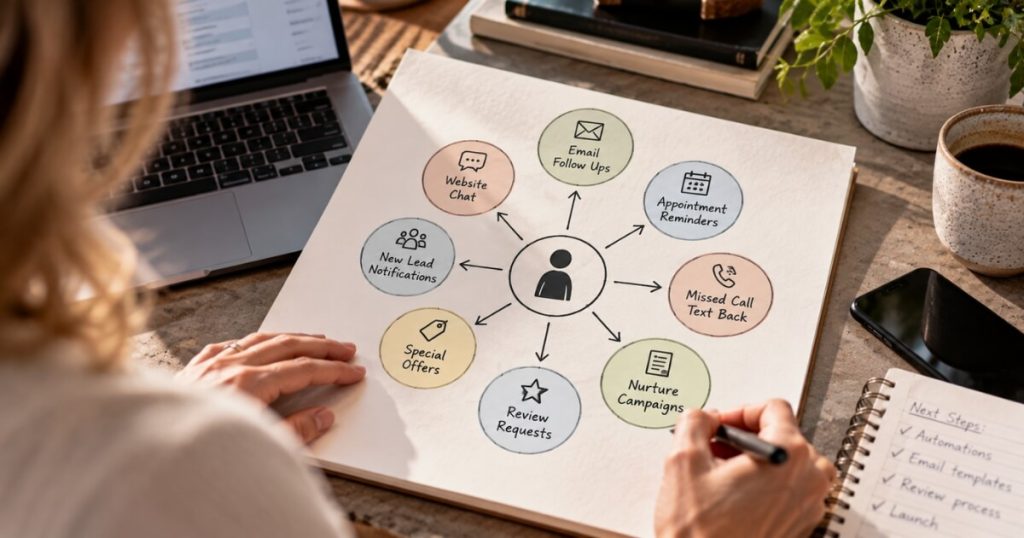
The plumbing around the humans: link delivery, reminders, and no-show recovery.
The build from this call was all live in the CRM.
When a lead replies “text,” the booking link sends automatically — the human stays in the loop, the busywork doesn’t.
Appointment reminders run on a set cadence.
And no-shows get their own pipeline stage with an automated reschedule text: “if Marie no-showed… here’s a link that you can reschedule on.”
Track no-shows first, then build automations from what the data shows.
That’s the pattern that works today: humans own the conversation and the commitment; automation owns the delivery and the chasing.
It’s the same division of labor behind every high-converting patient acquisition system we build — automate the follow-through, never the relationship.
How do I stop weight-loss emails going to my TRT patients?
Tag every patient by service at intake and filter every automation on the tag.
This clinic’s rule: “I’d rather have them get nothing than the wrong stuff.”
Multi-service clinics break their own nurture the moment one generic sequence hits everyone.
This one runs weight loss, TRT, HRT, peptides, and longevity across multiple locations.
A TRT patient getting semaglutide promos learns to ignore you — or unsubscribes the week you had something relevant.
Service tags at intake cost one dropdown question and buy you segmentation forever.
The bonus: the dropdown itself generates revenue intelligence.
Adding “what service are you interested in?” to the intake form surfaced this clinic’s first-ever longevity lead — a $13,000 program — plus two TRT leads in the first month.
Patients will tell you what they want to buy if the form asks.

Do I need a separate patient pipeline for each service line?
Yes — but clone, don’t invent.
Same skeleton, different cadence and content.
This clinic’s weight-loss pipeline became the template for TRT and HRT versions.
The weight-loss pipeline tracks first orders through refill checkpoints, with SMS touches at one week, two weeks, four weeks, then repeating.
The TRT and HRT versions follow an identical structure with service-appropriate messaging.
The refill math shows why the pipeline matters more than lead generation at a certain scale.
In one month, this clinic “gained 50 and lost 50” refills — a leaky bucket that no amount of new leads fixes.
Retention pipelines are where recurring-revenue clinics actually compound.
The clinic grew from 360 to about 400 patients in the month this system tightened.
When will AI booking be good enough to trust?
When its show rates approach human-booked levels — measure it, don’t vibe it.
We’re “very optimistic that it will get there.”
The models improve monthly, and the plumbing use cases — drafting replies, routing, and summarizing calls — are already useful.
But the calendar is the revenue engine of a cash-pay practice, and the test is empirical.
Run AI booking on a slice of lead flow, compare show rates against your human baseline, and let the difference decide.
At 20% vs. 90%, the answer today is a human with automated support — not a bot with a login to your calendar.
FAQ’s About AI Booking and Clinic Automation
What show rate should a cash-pay clinic expect on human-booked appointments?
Around 90% when a person books it and reminders run on cadence.
That’s the live benchmark from the largest weight-loss clinic in our portfolio.
If your human-booked show rate is materially lower, fix reminders and deposits before considering staffing changes.
Is an AI receptionist the same as AI booking?
No.
Answering questions, routing calls, and capturing contact information is lower-stakes and works reasonably well today.
The failure mode in our data is specifically the booking commitment — the step where show rate gets made.
What’s the cheapest automation with the biggest booking impact?
Auto-sending the booking link the moment a lead texts back, plus a 2-day/1-day/2-hour reminder cadence.
Zero conversation risk, immediate show-rate lift.
How should no-shows be handled automatically?
Move them to a dedicated no-show stage that triggers a reschedule text with a self-serve link.
Track the stage for a month first.
The data tells you whether you have a reminder problem, a deposit problem, or a booking-source problem.
Does asking “what service are you interested in?” on the intake form hurt conversion?
In this clinic’s first month, it did the opposite.
The dropdown surfaced a $13,000 longevity lead and two TRT leads that would otherwise have entered a generic weight-loss funnel.
One question, three high-value patients correctly routed.
What’s the next step?
If you’re weighing an AI receptionist because the front desk is drowning, the fix that works today is sharper: humans on commitments, automation on everything else.
Book a strategy call.
In 60 minutes we’ll map your booking flow, set up the no-show recovery and reminder cadence, and — if you want to test AI booking — design the show-rate experiment so the data makes the call.